

Feature first published in the January–February 2021 issue of 3D ADEPT MAG. Roles, products, outlooks and interviews reflect that period. Applications need distinguishing by intended use: working model, procedural tool or patient device.
3D printing complements digital manufacturing tools in dental laboratories. What progress does it offer, and what cost, training or validation challenges remain? This 2021 feature combines the perspectives of Stijn Hanssen, Sales, Marketing & Applications Manager at 3D Systems, and Mayra Vasques, founder of Innov3D.
Adoption depends on more than the printer. It requires skills in data acquisition, design, manufacturing and inspection, alongside an appropriate laboratory workflow.
A SmarTech study published in 2018 projected a $9.5 billion dental 3D printing market in 2027. This was a forecast made at that time, not an achieved figure or a profitability guarantee for a practice.
Main manufacturing tools used in a dental lab
A digital workflow begins with data acquisition, followed by design and manufacturing preparation. Intraoral or laboratory optical scanning describes surfaces; tomography, including CBCT, provides volumetric data. These data are not interchangeable, and software does not replace acquisition. CBCT uses ionising radiation and is selected according to clinical need, rather than routinely for every print. Hanssen explains:
“dentistry is going through fundamental changes, starting with analogue methods and moving towards digital workflows with digital scanning, design, 3D printing materials. Traditional lines are being blurred in the dental field. We think that most dental care providers will find the use for an intraoral scanner as a more accurate and convenient alternative to analogue impression materials. For the scanning process there are several options depending on the clients’ case; scanning an impression or intra oral scanning. Key is what is done with the scan afterwards. The accuracy in design and in printing is very important for a better patient outcome.”

As a user, Vasques believes that a dental 3D scanner continues to have a unique role to play in the digital workflow: “The digital workflow in dentistry consists in 3 steps: data acquisition, design, and manufacture. I´m used to explain this as, first you must transform the real into digital by data acquisition, then you will be able to create your project using the design software and after that you will turn this virtual project into reality using digital manufacturing. Affordable dental 3D printers make it possible to spread this technology in dentistry and improve the in-office 3D printing modality, but they are not a substitute for the 3D scanner, each one belongs to a different part of the process.”
Stereolithography (SLA) and digital light processing (DLP) are vat photopolymerisation processes. Selection should account for intended use, compatible resin, performance, traceability and validated post-processing rather than preference for a technology alone. Our resin 3D printing feature explains their principles.
Related coverage: dental applications and CONTEXT’s analysis of the printer market during Covid-19.
Other processes, including photopolymer jetting and metal printing, serve different uses. It is incorrect to describe metal printers as inherently insufficiently precise for dentistry: 3D Systems’ dental portfolio already included the DMP Dental 100 in 2019. A working model and a patient device do not require the same material or validation; each manufacturing chain needs assessing for its intended use.
Speaking of the main tools a clinician may use before and after the printing process of a model, Vasques explains:
“The ideal process requires an intraoral scanner to obtain patients digital cast and a resin 3D Printer (SLA or DLP technologies) due to accuracy and the different options of biocompatible resins. To complete the process successfully, it´s necessary to carefully proceed the post processing method washing the printed parts properly and post-curing to reach the best characteristics of the materials.”
Material, printer, cleaning and post-curing must form a validated chain for the intended use, following applicable instructions. Describing a resin as biocompatible does not by itself establish compliance of the finished device. The FDA’s 2017 guidance addresses testing and post-processing of additively manufactured devices.
Applications and production
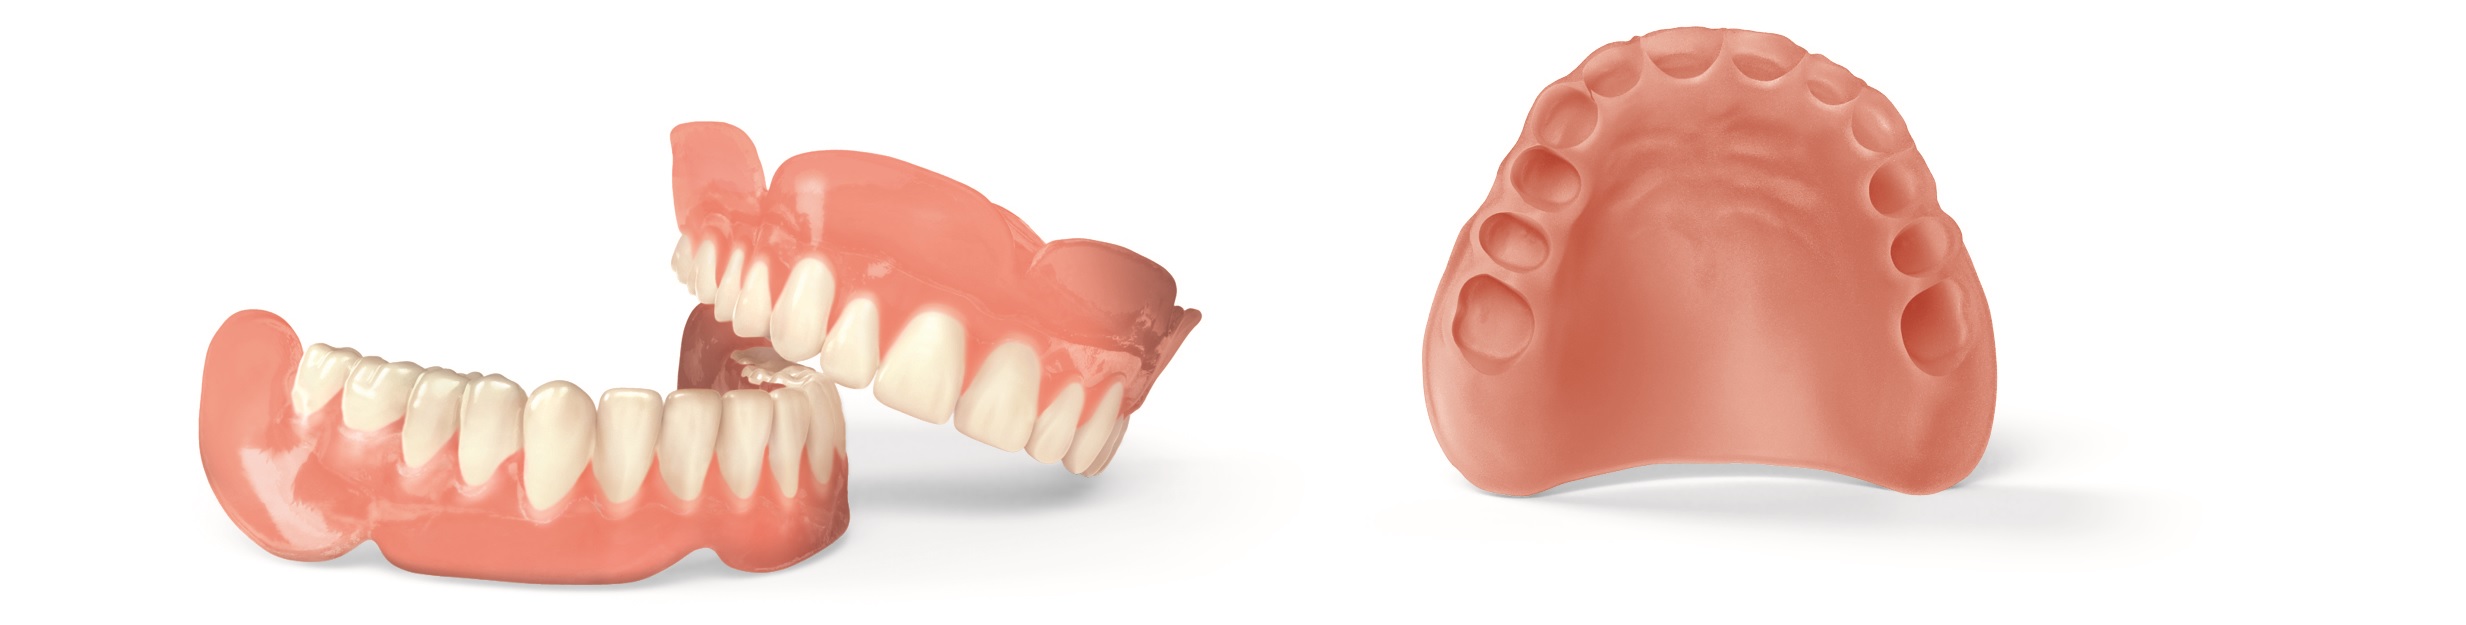
Uses include models, guides, provisional restorations, selected prostheses and splints, depending on validated materials and processes. In 2021, clear aligners were notably thermoformed over printed models: this does not mean the aligner itself was directly printed. Vasques proposes two broad categories: “The first category comprises products that will be used over a long period of time inside the mouth. They include for instance dental prosthesis, aligners and night guards. The second category comprises products intended for procedures. They include surgical guides and a wide range of other guides such as bio models and customized instruments. There is a lot of room to innovate to create new techniques and new solutions”.
Hanssen describes the applications observed by 3D Systems for its dental portfolio:
“We see a big utilization of 3D printing for temporary or final prosthetics. Dentures have also been an incredible growth market since last year and night guards are gaining popularity.” Moreover, according to the manufacturer, orthodontic tooling models for thermoforming are the applications that require volume production the most. Anatomical modelling is another use. CBCT data may contribute where the examination is clinically justified; it is not a mandatory step in every dental manufacturing workflow.

Producing an anatomical replica requires processing and segmenting volumetric data, converting it into a printable model and checking it. This is not simply sending an image directly to a printer. The examination’s suitability needs assessing for the patient, as set out in the IAEA’s radiation protection principles.
Customisation needs accuracy, repeatability and traceability checks. High volumes can involve many unique parts, each associated with a patient; data management and protection are therefore part of the workflow.
Challenges and future outlooks
Increasing volumes requires an appropriate organisation, not necessarily a printer farm in every practice. Needs depend on demand, skills, maintenance and outsourcing options. Vasques highlights better logistics and equipment that reduce the clinician’s production workload.
In the meantime, she states that the current area for improvement should be the type and quality of materials for long-term intraoral use. “Dental professionals are more and more open to new technologies, but most of them relate that they are not secure with the longevity and safety of the 3D printed parts”, she adds.
This observation reflects the interviewee’s experience; it is not a representative survey of the entire profession.
On the other hand, as 3D Systems is working on new materials and 3D printers’ development, Hanssen points out the need for education and training to help advance the utilization of 3D printing among clinicians and dental specialists.
“Dental 3D printing will play an important part in the digital future of dentistry as 3D printing materials will become more advanced and the number of applications will grow. Due to Covid-19, we all aim to assist dental practices to reduce contact with patients. Working with digital patient data helps to reduce patient chair time and improves safety for both patient and practise”, he completes.
This pandemic-era outlook does not establish reduced infection risk for every procedure. Digitisation does not replace the prevention measures applicable to care.
It would be incorrect to conclude that no regulatory framework existed. The FDA published technical guidance for additively manufactured devices in December 2017. In the European Union, Regulation 2017/745, already adopted at the time of this interview, became applicable on 26 May 2021. Requirements depend on the device and its intended use; 3D printing does not remove them.
This exclusive feature has first been published in the 2021 January/February issue of 3D ADEPT Mag.
THE 3D ADEPT WEEKLY NEWSLETTER
The industry moves fast. Stay ahead.
Every week, the latest additive manufacturing news, in-depth features and real-world applications, straight to your inbox. Plus, be the first to know when a new issue of 3D ADEPT Mag is out.
Free · One email a week · Unsubscribe anytime
Clicking loads our email provider’s sign-up form, including its analytics and Google’s anti-bot protection. You’re only subscribed if you complete the sign-up. Read our privacy policy.