
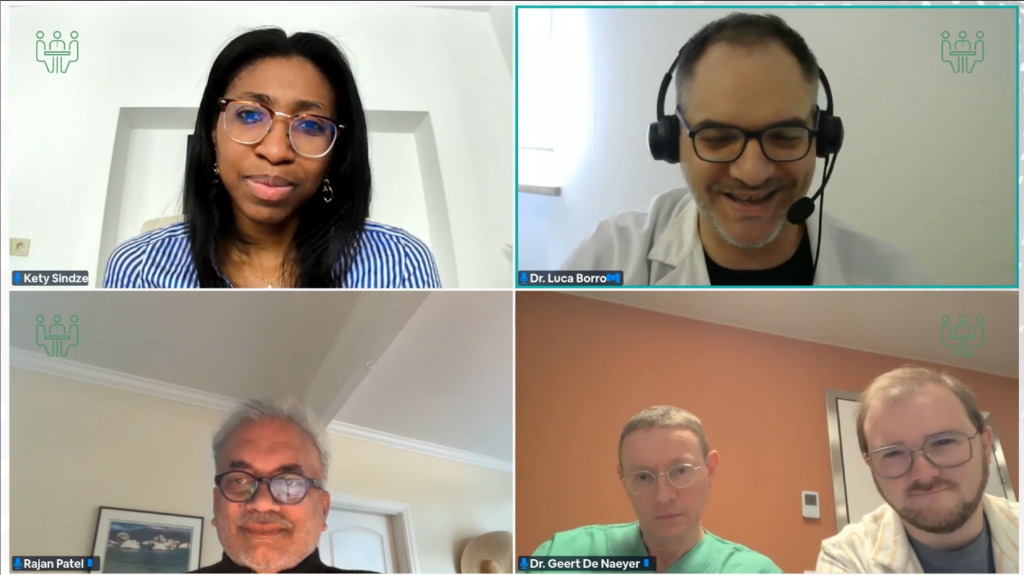
Dr. Luca Borro (Bambino Gesù Pediatric Hospital), Rajan Patel (Kallisio) and Dr. Geert De Naeyer (AZORG Hospital) joined the latest Additive Talks session. De Naeyer was accompanied by our mystery guest, Wesly Jacobs, founder of PrintPlace.
You may remember that, not so long ago, Azorg Hospitals decided to bring 3D printing in-house through the establishment of PrintPlace on one of its campuses. This move has been fundamental and as we learned from this discussion, has led to a number of projects being developed in-house right now.
As these panelists are all from a different background, we were expecting different takes on what it really takes to deploy AM in healthcare. And we got them across two specific areas: where the real bottleneck lies and what “scaling” means.
Where the real bottleneck lies.
For Rajan Patel, the technology is already mature enough to scale; the challenge is convincing hospitals to treat patient-specific devices as part of a sustainable economic model rather than a procurement expense.
In Luca Borro and Wesly Jacobs’ view, the biggest hurdle is regulatory ambiguity and operational integration inside hospitals. Borro stresses that hospitals are not medical device manufacturers. For this reason, turning exceptional, compassionate-use projects into routine clinical practice remains extremely difficult.
Jacobs goes further, suggesting that Europe still leaves too much room for interpretation, forcing hospitals and suppliers to build compliance frameworks almost from scratch.
From a clinical perspective, Geert De Naeyer reminds us of something we have heard multiple times: the problem is often solved quickly through collaboration between doctors and engineers, while the regulatory ecosystem introduces the real complexity.
What scaling means for the experts
Patel views “scale” as a standardized workflow capable of producing thousands of individualized devices, similar to prescription lenses or dental aligners.
De Naeyer and Jacobs, however, focus on the technology itself and see additive manufacturing as a way to solve the “long tail” of healthcare problems (low-volume, highly specific clinical needs that traditional manufacturers would never address economically).
In that sense, they imply that success is not necessarily measured by mass production, but by the ability to respond rapidly to unique patient situations across multiple hospital sites. Borro’s pediatric perspective reinforces this approach: children’s anatomical variability makes standardization harder, yet also makes patient-specific manufacturing more valuable.
This unresolved debate is precisely what makes the rest of the panel worth watching.
Watch below for more insights
The main conversation takes place until the 30th minute of the video linked below, and is followed by several questions from the audience that the experts answered.
Watch the Additive Talks session: The path to clinical scale
THE 3D ADEPT WEEKLY NEWSLETTER
The industry moves fast. Stay ahead.
Every week, the latest additive manufacturing news, in-depth features and real-world applications, straight to your inbox. Plus, be the first to know when a new issue of 3D ADEPT Mag is out.
Free · One email a week · Unsubscribe anytime
Clicking loads our email provider’s sign-up form, including its analytics and Google’s anti-bot protection. You’re only subscribed if you complete the sign-up. Read our privacy policy.