
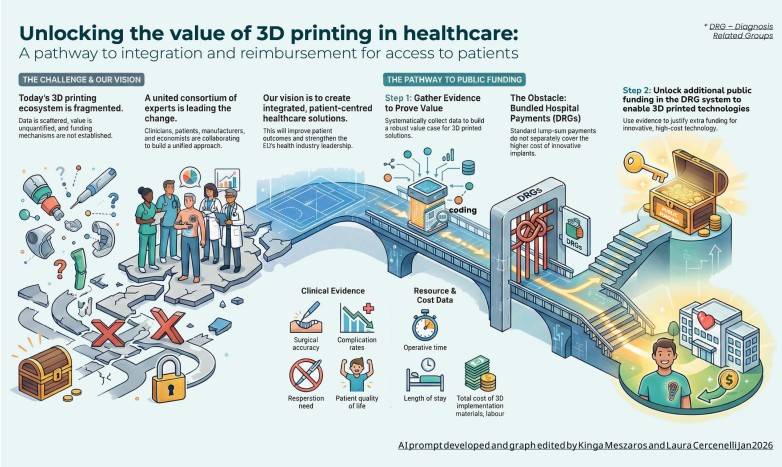
There is a particular frustration that intensifies in hospital corridors, point-of-care labs, and boardrooms across Europe. It is the frustration of people who see potential clinical value in a 3D-printed patient-specific device. Yet they cannot get the system to agree.
We have been following this conversation for some time. In a previous dossier, we explored the current state of public policies that help patients benefit from 3D-printed implants, mapping a landscape of national fragmentation, regulatory uncertainty, and missed connections between innovators and payers.
What we found, above all, was a technology maturing faster than the frameworks designed to absorb it. We also found countries working in silos to get 3D printing approved by healthcare systems.
This dossier picks up where that conversation left off and goes deeper.
Three perspectives on reimbursement
We spoke with three experts who each hold a piece of this puzzle:
- Kinga Meszaros brings the health economics lens, grounding the reimbursement debate in how European payers actually make decisions.
- Laura Cercenelli speaks from inside a university hospital point-of-care 3D printing lab in Emilia-Romagna, Italy, where the gap between what clinicians ask for daily and what the system is willing to fund is felt in very concrete terms.
- And Naomi Nathan, as a convener through Medical Goes Additive (MGA), has made it her work to ensure that – all relevant stakeholders; hospitals, manufacturers, researchers, and policymakers stop talking past each other and start building something together.
We understood the list of barriers to address. Through this dossier, we explain these barriers and the main stakeholders involved, and map what needs to happen next, and who needs to show up to make it possible.
Who should read this dossier, and what they will take away:
- Additive manufacturing companies and technology providers will find a clear articulation of why evidence generation is mandatory in this journey and what a well-structured economic argumentation for payers requires. Most importantly, this dossier emphasizes that the reimbursement conversation is not happening without you, but it cannot be led by you alone.
- Hospital administrators, clinicians, and point-of-care lab managers will recognize the structural challenges described here and hopefully, find frameworks that can help them make the case for funding, from DRG logic to coding strategies to multi-center evidence design.
- Health economists, HTA bodies, and payers will understand how the 3D printing field is working to speak their language and where the evidentiary gaps remain that their decisions depend on.
- Policymakers and European institutions will see both the fragmentation that needs addressing at a systemic level, and the collaborative project models, including the Innovative Health Initiative – Public-Private Partnership (PPP) funding mechanisms, already working to bridge it.
The system is not ready yet. But the people determined to change are organized, rigorous, and increasingly aligned. This is their conversation.
Part I | The health economics perspective: Speaking the language payers understand
Based on the expertise of Kinga Meszaros, Health economics and policy professional with focus on European health and social systems.
The journey from innovation to access is a two-step process most AM companies misunderstand.
For a health technology to become broadly accessible through publicly funded care, regulatory requirements and funding decisions both matter. Their routes differ between medicines, devices and clinical services.
Regulatory access: meeting the applicable safety, performance and other legal requirements. In the EU, medicines follow either national authorization procedures or a centralized procedure, with European Commission authorization after assessment by the European Medicines Agency (EMA). Medical devices generally follow the CE marking framework, with specific provisions for qualifying in-house devices.

But clearing that first gate does not open the door to patients. As Kinga Meszaros explains: “Once a product is available on the market, the next question is: is it something that can be widely used in the setting of healthcare? And that is driven by two aspects. One is that the clinical community includes it in their practice, for example in their clinical guidelines. The other is that there is public funding to cover the costs, so that patients can actually access the intervention and afford in case of any need for co-payment.”
Public funding: Complexity begins here, and the additive manufacturing community is still learning the rules.
In Europe, decisions on public reimbursement are made within national healthcare systems, with responsibilities that can also lie at regional level. Each member state manages its own healthcare budget, its own coverage logic, and most of the countries have their own HTA (Health Technology Assessment) body. The result, as Meszaros puts it plainly, is a system that is “very heterogeneous within the different countries.”
For medicines, the reimbursement pathway, while variable, follows a relatively established logic in most of the countries: a manufacturer submits a dossier, an HTA body evaluates clinical and economic evidence, a decision is made.
For medical devices, funding can operate through hospital budgets, procedure payments or separate arrangements. In some hospital settings, a device’s cost is included in a diagnosis-related group payment. The applicable route varies between health systems and care settings.
The DRG problem: Why 3D printing doesn’t show up in healthcare budgets

Diagnosis-related groups, or DRGs, classify hospital cases and are used in various European payment systems. In a case-based payment arrangement, several elements of care can be covered by a single payment. Countries also use budgets, daily rates and mixed models; there is no single DRG payment rule for Europe.
Meszaros offers a vivid illustration: “That DRG code for, say, a spinal surgery includes the cost of cleaning, the electricity bill of the operating room, the payments for the healthcare professionals and it includes the surgical guide, or the implant itself as needed.”
This is where the issue described by Meszaros can arise. If a patient-specific implant adds costs that are not covered by a tariff adjustment or separate funding, a hospital may struggle to absorb those costs even when clinicians expect benefits. That is a potential funding barrier, rather than an inevitable choice between financial loss and abandoning innovation in every system.
A separately reimbursed product can have an identifiable payment line, while a surgical guide included in a bundled hospital payment may have no distinct reimbursement. This contrast depends on the product and payment setting; it is not a universal distinction between medicines and medical devices.
Medicine vs. medical device vs. 3D print-enabled personalized care: why these distinctions matter
Meszaros insists on a clarification that may seem technical but has real consequences.
A medicine or vaccine has an identifiable cost, a predictable dosage, and an established reimbursement logic. A standard medical device may be included in a hospital payment bundle, while its regulatory route remains a separate question. A personalized, 3D-printed enabled device introduces a third layer of complexity: it is not a product in the traditional sense. It is a technology applied within a surgical flow, customized to an individual, and often co-produced by a combination of hospital staff, external software, and manufacturing infrastructure.
“3D enabling or personalization itself is a technology,” Meszaros notes. “It’s not a product itself, it’s not a service itself – it is a potentially value-adding feature of them. This technology can be used across several disease areas and phases of the surgical flow, and is seen still as part of the same flow in the respective solution, including the service and product, under an existing DRG..”
This cross-cutting nature of AM as a technology platform (not a single product for a single indication) creates a market access challenge unlike anything payers have typically dealt with. Building a reimbursement pathway requires thinking at the level of surgical flows and value frameworks.
What “value” actually means to a payer and why AM companies do not speak that language

When a European payer looks at a 3D print-enabled surgical intervention and asks whether it justifies additional funding, they are running a specific mental calculation. What is the measurable health outcome improvement or cost saving compared to the standard solution that justifies that premium?
As Meszaros explains, payers are accustomed to comparing technologies in a structured way: “The payer thinks: what is the better health outcome that can justify that amount of money? How many days less does hospitalization take? How much faster is the surgical intervention taking place, freeing up resources for other interventions? How much less rehospitalization occurs one year after the surgery?”
The data answering these questions feed into cost-effectiveness models. These tools allow payers to compare investment in a 3D print-enabled spine procedure against, say, an oncology treatment or a cardiovascular drug. They express results using a common denominator: the cost of one unit of health gain (incremental cost-effectiveness ratio).
What would a well-structured economic case for a 3D-printed orthopedic implant actually look like? According to Meszaros, it would need to map and quantify the full costs and health outcomes of the entire surgical flow, from pre-operative planning (anatomical models, surgical guides) through the procedure itself to recovery and follow-up.
It would require data collection and modelling studies to help establish those cost-effectiveness ratios and budget impact results. And it would need to demonstrate value in a language payers already use: quality-adjusted life years, complication rates, re-hospitalization rates, surgical accuracy metrics and budget impact.
The challenge is that most studies in the AM field, while increasingly robust on the clinical side, do not (always) have a solid economic dimension. “Most of these scientific papers are more focused on clinical evidence,” Laura Cercenelli confirms. “The lack is, in part, probably the economic evidence.”
The IHI framework, described in more detail below, can support collaborative research to help close that gap.
A word for AM companies: your role in building the evidence base
One of the most direct messages to emerge from this conversation was addressed implicitly to AM technology providers. The reimbursement pathway will not be built on clinical enthusiasm alone. Manufacturers who believe their solutions deliver better outcomes but cannot demonstrate it in the language the system requires are, in practical terms, not yet ready for the healthcare system.
“Manufacturers must align on their perception of value,” the background materials from Meszaros state, “and provide shared data comparing their technology to the standard of care.” That means participating in the evidence-building process, including multi-stakeholder consortia, data collection aligned with registry frameworks, and economic evaluations conducted in collaboration with health economists and hospital finance experts.
The good news: there is a structural parallel that offers encouragement. Robotic surgery navigates this pathway. The stakeholders got together, and shared relevant case studies to be discussed with broad stakeholders in this white paper.
With that example, I trust AM technology providers can do their homework.
Part II | Clinical Evidence: Assessing the value clinicians see
Based on the expertise of Laura Cercenelli, biomedical engineer and senior staff at eDIMES Lab, a university hospital 3D point-of-care lab led by Prof. Emanuela Marcelli, in Bologna, Emilia-Romagna, Italy

Ask a clinician when the question of reimbursement first enters the room, and the answer reveals a great deal about the current state of 3D printing in healthcare.
For Laura Cercenelli, whose point-of-care lab produces anatomical models and patient-specific surgical aids for surgeons across multiple specialties, the answer is clear: reimbursement becomes an urgent conversation at the moment of scaling.
“The topic of reimbursement usually emerges when there is a need to move from a single case or pilot use toward broader implementation,” she explains. “The question comes mainly from the hospital administration, in close collaboration with clinicians and 3D PoC lab staff since they perceive the clinical value and workflow impact.”
It is worth pausing on that dynamic: The clinician perceives the value and asks for the technology. The 3D lab delivers it. The administration looks at the accumulating costs and asks: how do we pay for this? That sequence (value first, cost conversation second) is both understandable and structurally problematic. By the time the reimbursement question enters the room, clinicians are already using the technology and the costs are accumulating. Yet the evidence base may not be in place to justify formal funding.
From anatomical models to surgical guides to implants: the spectrum that doesn’t yet have a single solution
One of Cercenelli’s most important contributions to this conversation is a clarification between anatomical models, surgical guides, implants and their rapport with reimbursement.
She draws a clear progression: at one end, anatomical models used for preoperative planning; in the middle, 3D-printed cutting guides and surgical aids that help the surgeon during the intervention; at the far end, patient-specific implants; the full surgical flow from design through manufacturing to implantation.
Each level represents a different degree of complexity, a different regulatory status, and, interestingly, a different relationship to the current reimbursement landscape. “Reimbursement models should be structured across different categories of 3D print-enabled personalized treatments,” Cercenelli argues, “ranging from 3D anatomical models for preoperative planning, to 3D-printed surgical aids, and ultimately to implants. These represent increasing levels of complexity, and should correspond to distinct billing codes and, likely, different reimbursement categories.”
Cercenelli describes an uneven picture in the settings she knows. Some pathways exist for complex orthopedic implants, while anatomical models and cutting guides may be produced without a separate payment. Clinicians’ confidence in these tools does not remove the need to demonstrate their value or identify how their costs are covered.
A concrete example: the megaprosthesis case from Emilia-Romagna
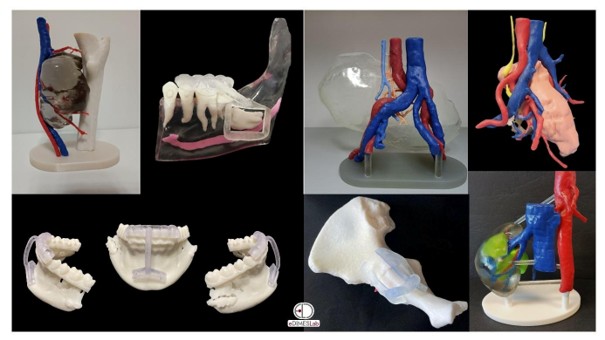
Cercenelli offers a specific, instructive example from her own region. In the orthopedic field in Emilia-Romagna, a specific category has been identified for custom-made prosthetics, the so-called “megaprostheses.”
In the regional example described by Cercenelli, the healthcare system provides an additional DRG payment above the standard implant reimbursement. The hospital receives a capped annual budget covering a predefined number of such cases, and clinicians decide, based on clinical indication, which patients benefit.
“In some sporadic examples, we have already established a sort of reimbursement,” Cercenelli notes, “but it is not a common practice in Italy and I think Europe is also fragmented in terms of recognizing the value of 3D personalization.”
This example reveals how local and contingent current solutions remain. A regional healthcare authority in one Italian region may have recognized the value of 3D printing here. But the hospital across the border operates under a different framework entirely. This is the fragmentation that any European-level solution has to overcome.
What “clinical evidence” actually means in a reimbursement dossier
The phrase “clinical evidence” is used frequently in discussions about AM in healthcare. Cercenelli is careful to define exactly what it needs to mean in the context of a reimbursement dossier, because the bar is higher, and the requirements more specific, than many in the AM field can tell.
“Clinical evidence needed for a reimbursement dossier goes well beyond safety and technical performance of the 3D-printed device. It’s really about demonstrating its value in real clinical practice.”
That means comparative outcomes versus the current standard of care, measured across multiple dimensions:
- Clinical outcomes (complication rates, revision rates, device durability),
- Patient-reported outcomes (quality of life, pain scores),
- Time and efficiency metrics (surgical time, procedural accuracy), and
- Resource utilization metrics (length of hospital stay, follow-up visits, direct costs of 3D implementation).
The last category, cost data, is where the literature is most thin. “Currently, the literature offers limited insight into these costs, as most studies focus primarily on clinical outcomes. This creates a significant gap in building robust economic evaluations.”
From single-center results to comparable evidence
For payers specifically, single-center studies can establish proof of concept, but they rarely suffice for coverage decisions. Personalization introduces variability: each patient, each device, each clinical setting is slightly different. This makes it harder to generalize from one center’s experience to a population-level recommendation.
Multi-center, comparative studies are needed. And those studies require something that is still underdeveloped across Europe: standardized frameworks for data collection, uniform coding systems, and coordinated protocols across institutions.
The orthopedic implant lifecycle: where the pathway breaks down
Walking through the lifecycle of a 3D-printed orthopedic implant reveals exactly where the system strains. The clinical and technical sequence is, by now, relatively well-defined: medical imaging and patient-specific design, design validation by clinician and engineer, additive manufacturing and post-processing, regulatory conformity assessment, implantation, and post-market follow-up.
“Technically, the pathway is quite well defined,” Cercenelli acknowledges. “Where things start to break down is on the regulatory and evidence side.”
From a regulatory standpoint, the classification questions — patient-matched versus custom-made device, in-house production versus outsourced manufacturing — remain inconsistently interpreted across EU member states. The MDR (Medical Device Regulation) introduced clearer frameworks, including Article 5.5 for in-house production, but their application varies.
From an evidence standpoint, the challenges are different for industry-driven implants than for point-of-care applications:
- For industry: data tends to be fragmented across centers, patient populations are small and heterogeneous, and controlled comparative studies are difficult to design.
- For PoC: the regulatory ambiguity compounds the evidence challenge, because variability in design, manufacturing, and clinical workflow across sites makes it harder to aggregate data in a standardized way.
Point-of-care manufacturing: the grey zone that needs a framework
For hospital teams, determining the applicable requirements for a device designed and manufactured in-house can be difficult. Such a product is not automatically outside medical-device regulation. Article 5, paragraph 5 of the EU Medical Device Regulation provides a conditional exemption from certain requirements for qualifying health institutions.
“Point-of-care production can introduce variability in design, manufacturing, and clinical workflows,” Cercenelli explains. “This reduces reproducibility and makes it more challenging to aggregate data in a standardized, comparable way that is meaningful for health economists.”
This can create a circular difficulty: variability in point-of-care practice and uncertainty over requirements can make comparable evidence harder to collect. It does not mean that hospital labs are categorically unable to produce evidence for health technology assessment.
Coding and tracking adoption
The solution Cercenelli points toward is twofold:
- First, shared frameworks and coding systems need to be developed: standardized identifiers for different types of 3D printing applications within electronic health record systems.
- Second, adoption itself needs to be traced systematically.
Whether we talk about point of care manufacturing or implants or surgical guides, the US provides a useful reference: Category III CPT codes for 3D-printed anatomical models and guides, and New Technology APC codes proposed by the American College of Radiology for 3D printing services, have created mechanisms to track usage and inform payment. Coding does not, however, guarantee reimbursement.
Editorial clarification — 26 September 2026: The ACR reported in September 2025 that initial 3D-printed model and guide codes could qualify for separate hospital outpatient payment under specified conditions, while add-on codes remained bundled. Its C8001 segmentation code excludes files intended for 3D printing. ACR coding and payment clarification.
“We should work together to set up registries to collect data, to trace the adoption of this technology, following the example from the United States,” Cercenelli urges. “Trying to identify some preliminary codes more related to tracing the usage of this technology; not yet directly related to reimbursement, but a starting point.”
The IHI Funding: enabling the evidence Europe needs
The practical obstacles to running multi-center randomized controlled studies for 3D-printed devices are real: standardization challenges across sites, small patient populations, workflow variability, regulatory differences between national frameworks, and the sheer coordination and funding required. Such undertakings require large multi-stakeholder consortia that bring together industry, hospitals, and academia to provide outcomes that payers and policymakers can act on.
The Innovative Health Initiative supports collaborative health research involving public and private participants. The account gathered for this dossier describes Medical Goes Additive bringing together more than forty stakeholders to explore a consortium intended to improve the evidence pathway toward reimbursement. That effort did not continue in the proposed form. The account points to a need for closer alignment within the 3D printing community, while Nathan’s stated goal remains better patient access. This should not be read as confirmation that an IHI-funded project had been awarded or completed.
Part III | Building the ecosystem: Convening the people who need to find each other

Based on the expertise of Naomi Nathan, Head of Medical, Medical Goes Additive (MgA)
“All our stakeholders romanticize reimbursement.“
Naomi Nathan’s framing of the challenge is characteristically direct. As she put it from the outset: “All our stakeholders romanticize reimbursement, yet they are unaware of the proper steps to take to enable it.”
It’s a point that deserves a moment of reflection: There is this common belief across the AM healthcare ecosystem, that demonstrating clinical value is sufficient to unlock funding. That if the technology works, the system will recognize it. Or that the evidence, once gathered, will speak for itself.
It does not. Healthcare systems are complex, politically administered, budget-constrained, and deeply conservative when it comes to adopting new funding categories. At the end of the day, 3D printing remains one among an array of health technology solutions. That’s why, the community has to go to the health economist, with evidence, with economic models, with coordinated advocacy.
What MgA actually does when it convenes stakeholders
Medical Goes Additive positions itself as a convener and it’s crucial to understand what the stakes actually require.
The stakeholders around the table in this field have different incentive structures, different timelines, and different definitions of success:
- Hospitals are focused on patient outcomes and operational sustainability.
- Device manufacturers are focused on market access and commercial viability.
- Health economists are focused on the frameworks that will allow payers to act.
- Regulators are focused on safety frameworks that may not yet fully account for personalized manufacturing at the point of care.
- And patients, who are, as Nathan emphasizes, “not really engaged” in these conversations to the degree they should be, are at the center of the entire exercise.

“If stakeholders are not aligned,” Nathan says, “we will continue having this fragmentation problem. Because everyone will be doing their own thing. And at the end of the day, health systems do not respond to that. We have to come together.”
In Nathan’s analysis, fragmentation is the core structural problem. Individual hospitals run their own registries. Manufacturers conduct their own studies. Meanwhile, countries fund pilot programs that never connect to broader evidence pools.
The 3D printing community is very fragmented for its size and tends to do things alone. As Nathan states, “everyone wants to do their own thing” and this, in terms of the goal we want to achieve, is counterproductive.
“Even Big Pharma comes together to make sure that they have a collective effort. If the message is we want to really tackle this problem, we have to collaborate and make it work and not have siloed approaches,” she adds.
The language gap is closing slowly
The language gap, Nathan believes, has begun to close. The presence of economists like Kinga Meszaros, the work of PoC labs like Cercenelli’s on evidence generation, the IHI framework’s structured approach to multi-center studies…all of this represents the AM community investing in the translation work the system requires.
But the closing is not yet complete. “Payers still see us as people who are just printing toys,” Nathan says, frankly. “There is no credible evidence, and we all know that the healthcare system is quite complex. We have to do ourselves the duty of showing this to the healthcare system decision-makers, because they are already inundated with so much innovation.”
The patient gap: the most urgent frontier

If the language gap is beginning to close, the patient gap remains wide open.
“We don’t really engage with patients,” Nathan acknowledges. “And yes, that’s a big gap.”
Patient perspectives matter when assessing value: quality of life, pain, satisfaction and experience can complement clinical and economic outcomes. Patient-reported outcome measures can help capture those effects. The relevant evidence and participation requirements depend on the assessment framework; they should not be presented as one blanket obligation under the Medical Device Regulation or the AI Act for every 3D printing application.
Without patient engagement, without data on benefits to patients, on quality of life, on satisfaction, on expectations, on the lived experience of receiving a personalized device versus a standard one, the economic case for 3D print-enabled care is missing its most human dimension.
You cannot lobby without the patients. “You cannot go to the next stage, which is advocacy, without them,” Nathan insists. “This is really key.”
Standardization: necessary but not sufficient
I believe MGA’s role may sometimes extend to the standardization debate, which is where the structural work of ecosystem building meets the operational reality of diverse institutions.
Although standardization is necessary for several reasons, Nathan is careful not to overstate what standardization alone can achieve.
The funding dimension: two angles worth keeping in mind
When Nathan speaks about funding, she highlights two specific types of funding:
The first is public research and infrastructure funding, primarily from the European Commission. This is the funding that enables researchers like Cercenelli to generate the clinical and economic evidence the field needs, that supports the multi-center studies the IHI framework is designed to produce, and that develops the coding and registry infrastructure on which real-world evidence depends.
“If you Google ‘funding for additive manufacturing in healthcare,’ you don’t see it,” Nathan observes. “We need this kind of specialized funding to show that, if we go forward, this technology will be able to enter into health systems.”
Industry co-investment and shared infrastructure
The second is industry funding and co-investment, the commitment from manufacturers and technology providers to participate in joint evidence-building projects, to share data across competitive lines, and to accept that market access requires collective infrastructure investment. The IHI framework exemplifies this model: co-funded by the European Commission and co-supported by industry, it is neither purely public nor purely commercial.
Both funding streams are necessary. And both require the kind of aligned stakeholder ecosystem that MGA is working to build.
Europe has therefore a genuine interest in developing a robust, locally-grounded and competitive 3D-print-enabled healthcare manufacturing capability, both for patient benefit, and for industrial competitiveness.
Part IV: Key takeaways, and what we are watching next

Three perspectives, one shared diagnosis: the challenge of reimbursement for 3D-printed devices in Europe is not primarily a technical problem. Additive manufacturing is mature enough to be considered. We have covered thousands of applications that demonstrate it.
The challenge, in my view, remains a set of fragmented, underdeveloped, and sometimes misaligned systems that were not designed with personalized, technology-enabled care in mind.
From Kinga Meszaros, we learned that payers speak a specific language, and that the AM community needs to develop fluency in it. Where a payment bundle does not recognize additional upfront costs or later benefits, personalized technologies may face a funding disadvantage. Bridging that gap requires economic models, not just clinical data.
From Laura Cercenelli, we learned that the reimbursement challenge corresponds to different categories of 3D printing implementation. Anatomical models, surgical guides, and full patient-specific implants require differentiated approaches. The evidence architecture supporting reimbursement for these categories needs the same care as the devices themselves. It requires systematic, collaborative work, with a clear sense of what the payer will ultimately need to see.
From Naomi Nathan, we learned that collective action, with all relevant stakeholders is not a strategy of last resort; it is the only strategy. Healthcare systems respond to organized communities who have done the homework, built the evidence, and arrived at the table with a coherent ask.
Structural changes that would move this forward
Based on this conversation, three structural shifts would meaningfully accelerate the path to reimbursement for 3D print-enabled care in Europe.
First, a European coding and registry framework for 3D printing applications in healthcare. The US has begun this work with CPT Category III codes and APC codes for 3D printing services. Europe needs a comparable initiative, fit for its healthcare architecture, that allows adoption to be tracked systematically and evidence to be gathered at scale.
Second, explicit recognition of 3D print-enabled surgical flows as a distinct value category in HTA frameworks. Where personalized devices are absorbed into an existing payment bundle, their distinct value may be difficult to show. Dedicated assessment frameworks, or at minimum dedicated add-on payment mechanisms modeled on what exists in some regions for complex orthopedic cases, could help make that value visible to funding decision-makers.
Third, patient engagement as a formal requirement of AM healthcare programs.
What we are watching
Several developments warrant close attention in the months ahead:
The IHI framework remains a potential funding route for collaborative research in this space. The ability of such collaborations to deliver harmonized clinical and economic evidence across multiple European centers and clinical applications will be a defining test of whether collaborative evidence generation at scale is possible in this field.
The evolution of EU MDR implementation, particularly the interpretation of Article 5.5 for in-house production and the guidance being developed for custom-made devices, will shape what PoC labs can and cannot do, and how their output will be regulated and evidenced.
The US parallel, particularly around Medicare/Medicaid reimbursement for 3D-printed prosthetics and the coding frameworks the American College of Radiology has proposed, offers a useful reference point.
And perhaps most importantly: the conversations happening inside the ecosystem, between manufacturers and hospital finance teams, between PoC labs and health economists, between advocacy organizations and European Commission officials; in a nutshell, conversations where the real work of alignment is taking place.
This dossier is, in part, a record of some of those conversations. We intend to keep following them.
Responses from experts have been edited for brevity and clarity. This dossier was first published in the healthcare 3D printing edition of 3D ADEPT Mag.
References
- Baghbanian, A., Carter, D., & Merlin, T. (2025). Methods for the health technology assessment of complex interventions: A scoping review. PLOS One, 20. https://doi.org/10.1371/journal.pone.0315381
- Blüher, M., Saunders, S., Mittard, V., Torres, R., Davis, J., & Saunders, R. (2019). Critical Review of European Health-Economic Guidelines for the Health Technology Assessment of Medical Devices. Frontiers in Medicine, 6. https://doi.org/10.3389/fmed.2019.00278
- Cangelosi, M., Chahar, A., & Eggington, S. (2023). Evolving use of Health Technology Assessment in Medical Device Procurement – a Global Systematic Review. Value in Health. https://doi.org/10.1016/j.jval.2023.06.005
- Conrads-Frank, A. et al. (2022). Decision-analytic modeling for early health technology assessment of medical devices – a scoping review. GMS German Medical Science, 20. https://doi.org/10.3205/000313
- Dettori, J., Henrikson, N., & Ecker, E. (2009). Health technology assessment. International Journal of Technology Assessment in Health Care, 25. https://doi.org/10.1017/s0266462309090345
- Fernandez, J., De Boissieu, P., & Galbraith, M. (2025). Health Technology Assessment in Europe: a comparison of organizations and introduction to the European regulation. Presse médicale, 104282. https://doi.org/10.1016/j.lpm.2025.104282
- Hunter, A. et al. (2018). EUPATI Guidance for Patient Involvement in Medicines Research and Development: Health Technology Assessment. Frontiers in Medicine, 5. https://doi.org/10.3389/fmed.2018.00231
- Kirwin, E., Round, J., Bond, K., & McCabe, C. (2022). A Conceptual Framework for Life-Cycle Health Technology Assessment. Value in Health, 25(7). https://doi.org/10.1016/j.jval.2021.11.1373
- KCE Belgium (2022). Responsible use of high-risk medical devices: the example of 3D-printed medical devices. https://kce.fgov.be/en/publications/all-reports/responsible-use-of-high-risk-medical-devices-the-example-of-3d-printed-medical-devices
- Llorian, E. et al. (2023). Frameworks for Health Technology Assessment at an Early Stage of Product Development. Value in Health. https://doi.org/10.1016/j.jval.2023.03.009
- Ming, J. et al. (2022). Health technology assessment of medical devices: current landscape, challenges, and a way forward. Cost Effectiveness and Resource Allocation, 20. https://doi.org/10.1186/s12962-022-00389-6
- Pimenta, J., & Vieira, A. (2025). Selection and Prioritization of Medical Devices for HTA Evaluation: A Systematic Review. Applied Health Economics and Health Policy, 23. https://doi.org/10.1007/s40258-025-00981-w
- Polisena, J., Williams, D., & Ciani, O. (2019). Health technology assessment of medical devices. Clinical Engineering Handbook. https://doi.org/10.1016/b978-0-12-813467-2.00112-7
- Wale, J. et al. (2022). Can We Afford to Exclude Patients Throughout Health Technology Assessment? Frontiers in Medical Technology, 3. https://doi.org/10.3389/fmedt.2021.796344
- Other background materials and HTA reference framework: Kinga Meszaros, assisted with AI-based literature synthesis via Consensus (consensus.app). Research synthesis: Consensus NLP, Inc., 2026.
References: EMA: authorization of medicines, European Commission: in-house medical devices, Innovative Health Initiative.
THE 3D ADEPT WEEKLY NEWSLETTER
The industry moves fast. Stay ahead.
Every week, the latest additive manufacturing news, in-depth features and real-world applications, straight to your inbox. Plus, be the first to know when a new issue of 3D ADEPT Mag is out.
Free · One email a week · Unsubscribe anytime
Clicking loads our email provider’s sign-up form, including its analytics and Google’s anti-bot protection. You’re only subscribed if you complete the sign-up. Read our privacy policy.


